Rapid sequence intubation (RSI) is the preferred method of emergency airway management. It involves the near simultaneous administration of fast-acting induction and neuromuscular blocking agents to achieve optimal intubating conditions without the need for bag-mask ventilation. The following discussion of orotracheal intubation refers to RSI. Techniques for gum-elastic bougie insertion and nasotracheal intubation are also discussed.
INDICATIONS
 Failure to protect the airway
 Failure to maintain the airway
 Failure of ventilation
 Failure of oxygenation
 Predicted deterioration or anticipated clinical course requiring intubation
CONTRAINDICATIONS
 Orotracheal and Nasotracheal Intubation
 Total upper airway obstruction
 Total loss of facial landmarks
 Nasotracheal Intubation
 Apnea
 Basilar skull or facial fracture
 Neck trauma or cervical spine injury
 Head injury with suspected increased intracranial pressure (ICP)
 Nasal or nasopharyngeal obstruction
 Combative patients or patients in extremis
 Coagulopathy
 Pediatric patients
LANDMARKS
 Viewing the oropharynx from above, the tongue is the most anterior structure
 The pouchlike vallecula separates the tongue from the epiglottis, which sits above the larynx (FIGURE 1.1)
 The vocal cords sit as an inverted “V” within the larynx
 The larynx is anterior to the esophagus
TECHNIQUE FOR OROTRACHEAL INTUBATION
 General Basic Steps
 Preparation
 Preoxygenation
 Pretreatment
 Paralysis and induction
 Positioning
 Placement of tube
 Proof of placement
 Postintubation management
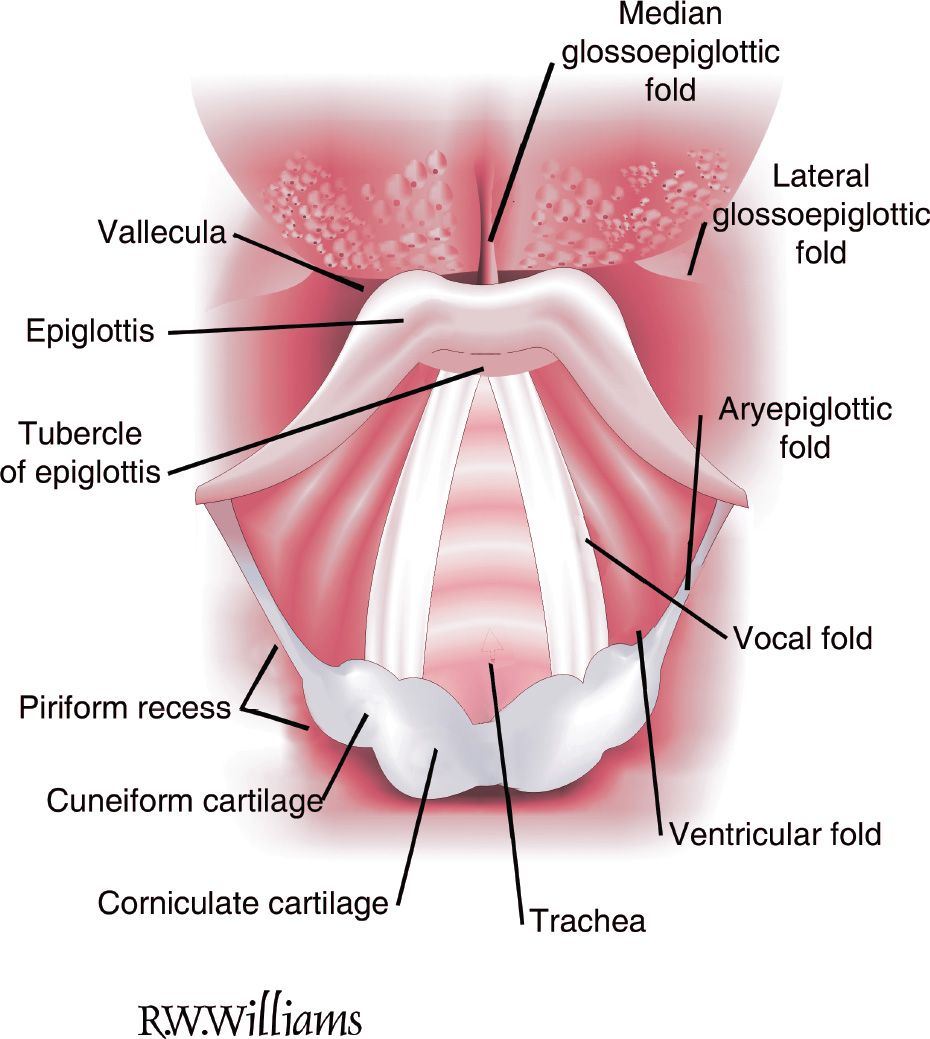
FIGURE 1.1 Larynx visualized from the oropharynx. Note the median glossoepiglottic fold. It is pressure on this structure by the tip of a curved blade that flips the epiglottis forward, exposing the glottis during laryngoscopy. Note that the valleculae and the pyriform recesses are different structures, a fact often confused in the anesthesia literature. The cuneiform and corniculate cartilages are called the arytenoid cartilages. The ridge between them posteriorly is called the posterior commissure. (Reused with permission from Redden RJ. Anatomic considerations in anesthesia. In: Hagberg CA, ed. Handbook of Difficult Airway Management. Philadelphia, PA: Churchill Livingstone; 2000:9.)
 Preparation
 Assess airway: Use LEMON mnemonic to predict difficulty of airway
 Look externally: If you sense that an airway appears difficult, it likely is
 Evaluate anatomy: The “3-3-2 rule” (FIGURE 1.2)
 Thyromental distance: Should be approximately 3 finger widths. Significantly more or less suggests a difficult airway.
 Mouth opening: Less than 3 finger widths predicts poor visualization on laryngoscopy and a difficult airway
 Hyomental distance: More or less than 2 finger widths predicts a difficult airway
 Mallampati score: Roughly correlates the view of internal oropharyngeal structures with intubation success. Graded as class I to IV (FIGURE 1.3).
 Obstruction/Obesity: Any evidence of upper airway obstruction heralds a difficult airway. Obesity is also associated with difficult laryngoscopy.
 Neck mobility: Crucial to obtaining the optimum view of the larynx. Hindrance to neck extension, including cervical spine immobilization, predicts difficulty in intubation.
 Equipment
 Endotracheal tube (ETT) and smaller backup (often 7.5 or 8.0 and 7.0)
 10-cc syringe
 Laryngoscope blade
 Laryngoscope handle
 Suction
 Rescue airway devices, including oral airway, gum-elastic bougie, and laryngeal mask airway
 RSI pharmacologic agents
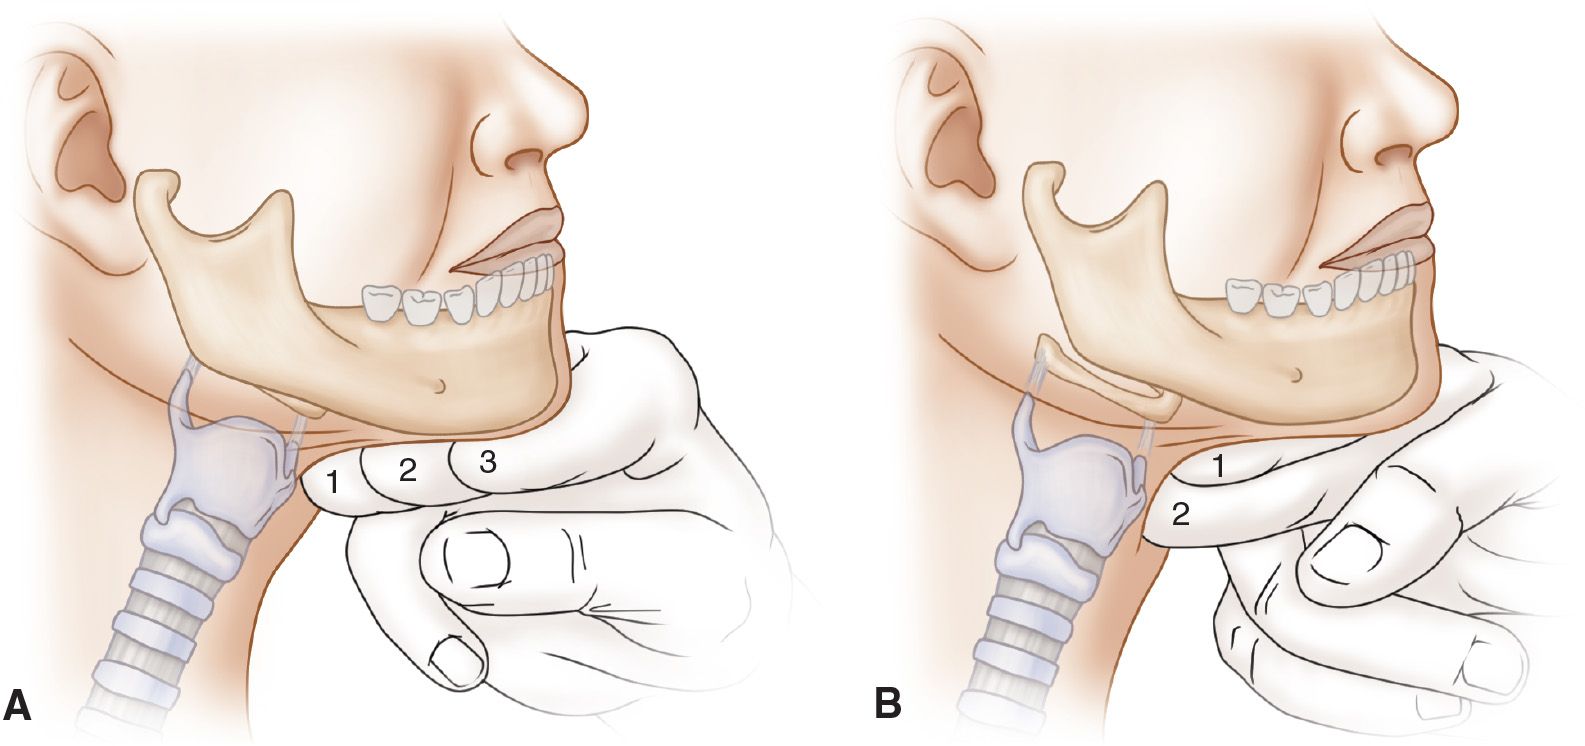
FIGURE 1.2 A: The second 3 of the 3-3-2 rule. B: The 2 of the 3-3-2 rule. (From Walls RM, Murphy MF. Manual of Emergency Airway Management. The 4th edition, 2012 version of the Walls Emergency Manual as well. Philadelphia, PA: Lippincott Williams & Wilkins; 2012:77, with permission.)
 Check integrity of ETT cuff
 Ensure that laryngoscope light source is working properly
 Make sure IV is functioning
 Ensure patient is appropriately monitored
 Position patient and adjust bed height
 Assign team roles
 Prepare for possible surgical airway
 Preoxygenation
 Theoretically, deliver 100% oxygen for 3 minutes via nonrebreather mask. (In reality, it delivers approximately 70% oxygen.)
 This fills the functional residual capacity with oxygen, replacing nitrogen and allowing for a longer apneic period before desaturation
 When time is critical, preoxygenation can be achieved in eight vital capacity breaths
 Nasal cannula should be placed to augment preoxygenation and facilitate apneic oxygenation
 Pretreatment
This refers to the administration of medications to attenuate the potential adverse side effects of intubation. Medications are given 3 minutes prior to intubation. While evidence supporting pretreatment is not conclusive, it should be considered in the following groups of patients:
 Elevated ICP: To mitigate ICP increase with laryngoscopy and intubation
 Lidocaine 1.5 mg/kg
 Fentanyl 3 μg/kg
 Cardiovascular disease: To decrease sympathetic response
 Fentanyl 3 μg/kg
 Reactive airway disease: To reduce bronchospasm
 Lidocaine 1.5 mg/kg
 Albuterol 2.5 mg nebulized
 Paralysis and Induction
 Give the induction agent, as a bolus, in sufficient dose to produce immediate loss of consciousness. Common agents are propofol (1.5–3 mg/kg) and etomidate (0.3 mg/kg).
 Push the paralytic agent immediately following the induction agent. Succinylcholine (1.5–2 mg/kg) is the common first choice in RSI because of its rapid onset.
 Fasciculations will occur 20 to 30 seconds after the administration of succinylcholine
 Apnea and paralysis will occur almost uniformly by 1 minute
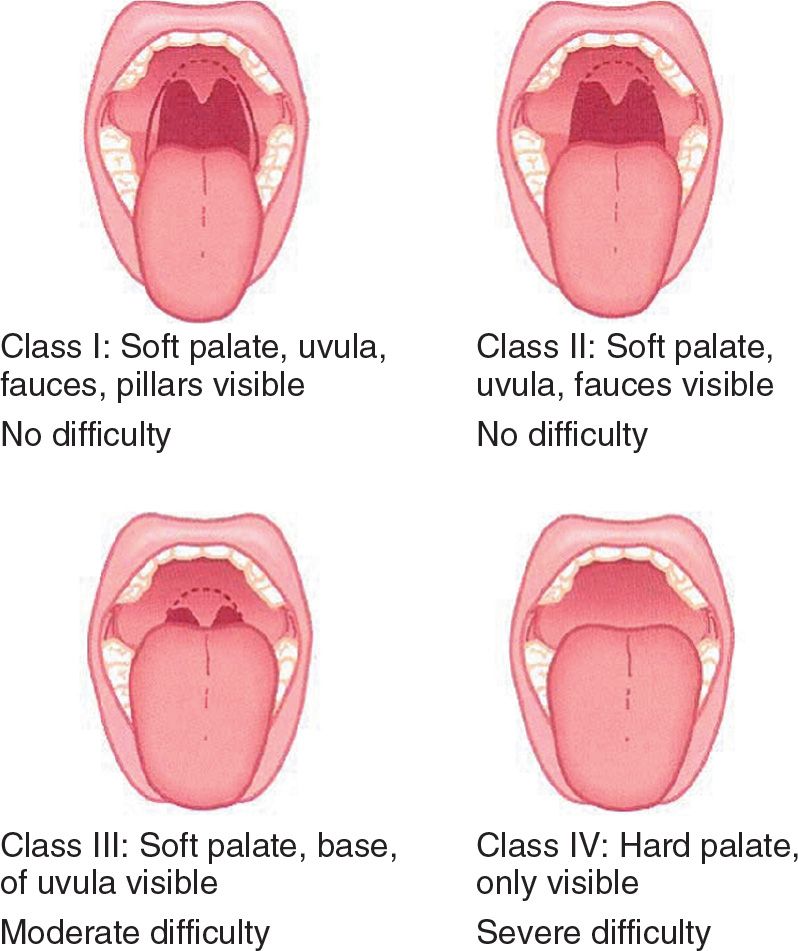
FIGURE 1.3 The Mallampati Scale. (From Walls RM, Murphy MF. Manual of Emergency Airway Management. 4th edition, 2012 version of the Walls Emergency Manual as well. Philadelphia, PA: Lippincott Williams & Wilkins; 2012:78, with permission.)



Full access? Get Clinical Tree


